
• Link to X
  • Link to Facebook
  • Link to Instagram
  • Link to TikTok
  • Link to Youtube
  • About
    • About Us
      • President
      • Board of Directors
      • Board of Advisors
      • Financials
      • Our Methodology
      • Success Tracker
      • Contact
  • Act Now
    • 30 Ways to Help
      • Contact Your Leader
      • Volunteer
      • Courses & Certificates
      • Be a Donor
    • Internships
      • In-Office Internships
      • Remote Internships
    • Legislation
      • Politics 101
  • The Blog
  • The Podcast
  • Magazine
  • Donate
  • Click to open the search input field Click to open the search input field Search
  • Menu Menu

Archive for category: Health

Information and stories on health topics.

Developing Countries, Disease, Global Poverty, Health

How Telemedicine Expands Healthcare in Rural Pakistan

Healthcare in Rural PakistanFor a patient living in a remote Pakistani community, seeing a doctor can require more than making an appointment. Long distances, transportation costs and limited access to specialists can make healthcare difficult to reach, especially for lower-income families. Telemedicine in Pakistan offers one solution by connecting patients with healthcare professionals through digital platforms and remote consultations.

Pakistan has begun moving telemedicine beyond individual online consultations and into local health facilities. Recent government initiatives show how digital health can connect rural communities with doctors while allowing nurses and other health workers to provide support on the ground. Here is more information about how telemedicine is expanding healthcare access in rural Pakistan.

Why Rural Communities Need Better Healthcare Access

Healthcare access in rural Pakistan is challenging due to significant barriers. The World Bank estimates that about 60.5% of Pakistan’s population lived in rural areas in 2025. Rural communities also experience higher poverty rates than urban communities, which makes the cost and accessibility of health services especially important.

For some rural patients, reaching a hospital or specialist requires a long journey. Transportation costs can add another burden for families with limited incomes. For people living in poverty, the cost of traveling to a distant hospital can also mean sacrificing money needed for food or other household necessities. Workers who depend on daily wages may also lose income when they have to spend a day traveling for medical care. These barriers can discourage people from seeking care or cause them to delay treatment.

Healthcare costs can create an additional burden for low-income families. According to the World Bank, poverty remains significantly higher in rural areas than in urban areas of Pakistan. Improving access to healthcare is therefore important not only for people’s health but also for protecting vulnerable families from additional financial pressure.

Telemedicine can address part of this problem. A 2024 study in “Frontiers in Public Health” found that telehealth can reduce travel-related costs and time while improving access to healthcare for people in rural and isolated areas.

How Telemedicine Brings Doctors Closer

Telemedicine allows patients to communicate with doctors without traveling to a distant hospital for every consultation. Depending on the service, patients can discuss symptoms, receive medical advice and access follow-up care through video calls or other digital platforms.

Sehat Kahani, a Pakistani digital health organization, uses a nurse-assisted e-clinic model to connect patients in underserved communities with doctors remotely. Nurses can assist patients at local clinics while doctors provide consultations through digital platforms.

The model also creates opportunities for doctors to serve patients from a distance. Sehat Kahani’s network includes thousands of doctors and its digital platform has delivered about 1 million consultations, according to 100X Impact Accelerator. The organization reports that women make up a majority of its trained doctors, including women who have returned to medical practice through flexible telehealth work.

This approach can address two problems at once: communities gain access to doctors while qualified medical professionals can provide care without working from a traditional hospital or clinic.

Pakistan Expands Digital Healthcare

Pakistan’s government has recently taken steps to integrate telemedicine into primary healthcare.

On Jan. 6, 2026, the Ministry of National Health Services, Regulations and Coordination worked with Sehat Kahani to launch a paperless, telemedicine-enabled Basic Health Unit in Gokina, Islamabad. The center uses secure video consultations, electronic medical records, digital prescriptions and pharmacy management systems. Nurses at the facility help patients through consultations and follow-up care.

The government expanded this effort on Jan. 14, 2026, when the Federal Health Minister inaugurated another digitalized telemedicine center at Bhambar Tarar near Islamabad. The Ministry of Health reported that the area had a Basic Health Unit but lacked a posted doctor. Residents previously needed more than an hour to reach major hospitals in Islamabad.

The new center allows residents to receive medical consultations locally. Health workers can also refer patients who need more advanced treatment to tertiary hospitals.

The government also announced an agreement with Sehat Kahani under which 5,000 online doctors will provide remote consultations. The government has described telemedicine as a permanent part of Pakistan’s national healthcare system and plans to establish 10 telemedicine centers.

A Solution With Room To Grow

Telemedicine cannot replace every form of medical care. Doctors still need to examine some patients in person and communities need reliable internet access, digital devices and trained health workers to use telemedicine effectively.

However, Pakistan’s recent initiatives show how the country can combine digital services with local health facilities. Instead of requiring every patient to travel to a major city, a local health center can connect patients with doctors elsewhere while nurses provide in-person support.

Telemedicine in Pakistan can also help reduce some of the financial burden associated with traveling long distances for healthcare. For low-income families, avoiding unnecessary transportation expenses and reducing time away from work can make medical consultations more accessible.

Sehat Kahani’s experience also shows that telemedicine can operate at scale. Its platform has already delivered about 1 million consultations while its network of doctors continues to connect patients with medical professionals across Pakistan.

Looking Ahead

As Pakistan expands its digital health infrastructure, telemedicine in Pakistan can help reduce some of the geographic and financial barriers that affect underserved communities. By bringing qualified doctors closer to patients through technology, Pakistan can move toward a healthcare system where access depends less on a person’s location or ability to travel and improve healthcare access in rural Pakistan.

– Afia Atif

Afia is based in Chenab Nagar, Pakistan and focuses on Technology and Global Health for The Borgen Project.

Photo: Wikimedia Commons

September 4, 2026
https://borgenproject.org/wp-content/uploads/borgen-project-logo.svg 0 0 Jennifer Philipp https://borgenproject.org/wp-content/uploads/borgen-project-logo.svg Jennifer Philipp2026-09-04 03:00:322026-09-04 02:18:14How Telemedicine Expands Healthcare in Rural Pakistan
Global Poverty, Health, HIV/AIDS

Positives of USAID Programs in Lesotho

USAID Programs in LesothoAid is a quintessential piece of economic development and growth, specifically in places like Africa, a continent with some of the most significant challenges to furthering economic growth and development. Lesotho is a lower-middle-income country with a population of 2.3 million, which is projected to increase by 29% by 2050. This is consistent with lower-income countries, where mothers have more children when they do not expect one or more to survive.

The most vulnerable groups in Lesotho are farmers, young girls and children and women. USAID programs in Lesotho such as USAID Global Health Supply Chain Program-Procurement and Supply Management Program (USAID GHSCP-PSMP), which started in 2016, promote effective supply chain management for HIV/AIDS medication. Other programs include the DREAM Initiative, which started educating young women and girls about HIV protection in 2016, and Bophelo Bo Botle or Good Health Activity, which began in 2024 and works to educate people on good health practices.

The Ways That Lesotho Benefited From US Foreign Assistance 

USAID programs in Lesotho have helped address the HIV/AIDS epidemic. According to Lesotho’s 2025 National HIV Estimates Report, new HIV infections declined by 83% between 2010 and 2024, with approximately 3,200 new infections estimated in 2024. While this progress reflects the country’s broader HIV response, U.S.-supported programs have contributed through prevention, education and treatment. Programs such as the Bophelo Bo Botle Activity and DREAM Initiative have provided HIV prevention education, while USAID’s Global Health Supply Chain Program-Procurement and Supply Management (GHSCP-PSM) has helped provide access to life-saving HIV treatment. By helping people prevent and manage HIV, these programs can support healthier communities and enable more people to participate in education and economic opportunities.

Data from the World Health Organization and UNAIDS indicate that Lesotho has made significant progress in its response to HIV/AIDS. At the same time, life expectancy in Lesotho has increased from 44.3 years in 2008 to 57.8 years in 2024. Despite this improvement, Lesotho’s life expectancy remains well below the global average of 73.48 years. The gap reflects the country’s broader health and development challenges, including poverty, limited access to health care and the ongoing impact of HIV/AIDS.

USAID programs in Lesotho have helped significantly with the HIV/AIDS epidemic, with the United States funding more than $100 million towards economic growth and development in Lesotho. For example, through the GHSCP-PSMP model, it has helped promote the proper management of HIV/AIDS medications, leading to an increased supply of sterile needles and medications for HIV treatment. It has also provided $63.4 million towards irrigation planning and infrastructure, and allocated $29.5 million to primary health care services, such as the DREAM Initiative. This could explain the upward trends in life expectancy data.

Bophelo Bo Botle

The Bophelo Bo Botle Activity started in 2024 in Lesotho. This program focuses on educating people in Lesotho on general good health practices by utilizing people-centered prevention, care and treatment. This program was unfortunately terminated in 2025 due to United States budget cuts and cuts to the PEPFAR program. With the program only running for a year, the program did not have many accomplishments.

The DREAM Initiative

The DREAM Initiative began in Lesotho in 2016, focusing on the factors making adolescent girls and young women vulnerable to HIV/AIDS. Such factors include “gender-based violence, exclusion from economic advancement opportunities and a lack of access to secondary education.” After three and a half years of implementation, new infections among adolescent girls and young women decreased by 71.4% in the two districts where the program was operational.

USAID GHSCP-PSMP

The USAID Global Health Supply Chain Program-Procurement and Supply Management Program (USAID GHSCP-PSMP) began in 2016 and is scheduled to end in September 2026. This program has promoted supply chain management of HIV/AIDS medication and treatments. The USAID GHSCP-PSMP provided continued availability of HIV treatment and tuberculosis treatment. As of 2020, “97% of HIV positive adults were receiving antiretroviral treatments and 92% were virally suppressed.”

Setbacks

All of this progress comes with a substantial budget cut for USAID programs in Lesotho, and in U.S. foreign assistance all around. In 2025, the U.S. gave $24.7 million in total aid to Lesotho. This is a stark difference from just three years prior, when it gave $150 million.

However, the Chinese government has been strengthening relationships with Lesotho, along with 53 other African countries, and implementing many educational and health-based practices through foreign aid. For example, in 2024, China and UNAIDS pioneered a joint campaign called “Eliminating the Triple Threat in Girls and Young Women in Lesotho,” which reached 20,000 young women and promised $2 million. This is very promising after the budget cuts the United States made.

China also introduced scholarships for Lesotho in 2025. These scholarships are helping create skilled workers and “ease the financial burden of overseas education.” This is very promising after the budget cuts the United States made.

Looking Forward

Considering the U.S. foreign aid cuts, USAID programs in Lesotho like the DREAM Initiative, GHSC-PSM and the Bophelo Bo Botle Activity may not be able to continue. Thankfully, China has stepped in and introduced new programs and initiatives geared towards economic growth and development in Lesotho.

– Lily K Gibson

Lily is based in Bristol, CT, USA and focuses on Global Health and Politics for The Borgen Project.

Photo: Pexels

September 3, 2026
https://borgenproject.org/wp-content/uploads/borgen-project-logo.svg 0 0 Jennifer Philipp https://borgenproject.org/wp-content/uploads/borgen-project-logo.svg Jennifer Philipp2026-09-03 01:30:312026-09-12 13:48:27Positives of USAID Programs in Lesotho
Disease, Global Poverty, Health

Malaria Vaccination Program in Rwanda Helps Families in Poverty 

Malaria Vaccination Program in RwandaThe consequences of malaria have recently continued to affect the lives of families across Rwanda. According to the World Food Programme (WFP) poverty affects 27.4% of Rwanda’s population. Being sick with this life-threatening disease can result in lost income due to absence from work, which is detrimental, as Rwandan’s household savings are essential to spend on treatment from clinics. The lack of the benefit of earning a household income has led to financial strain on Rwandan families and pushed them into extreme poverty. Nevertheless, the new malaria vaccination program in Rwanda has helped families out of poverty. Organizations such as GAVI and UNICEF fund this free rollout, which can secure domestic incomes and give families an opportunity for financial security.

Malaria’s Impact on Household Incomes

 Malaria has imposed an economic burden on Rwanda. The Rwanda Biomedical Center (RBC) has reported an increase in malaria prevalence in Rwanda, with the disease affecting 76 people per 1,000 population—equivalent to 7.6%—in the 2024/2025 period, up from 4.5% recorded in 2023/2024. This has reduced the country’s economic growth, as families struggle with higher costs for essential goods and services and lack basic needs, which will inevitably push them into deeper poverty. As seen in high-deprivation regions, the price of food, transportation and school equipment amplifies the strain on low household incomes. This situation forces families to choose between medical care and necessities. This situation can decrease Rwanda’s economy and lead to a lack of internal wealth that affects trade, infrastructure and levels of employability.

Government-Led Immunization Strategy

 Nevertheless, Rwanda’s Ministry of Health began its malaria vaccine program in 2024. RBC figures show that in 2025/2026, malaria cases stood at 928,616, down from 1,131,314 in 2024/2025, indicating a recent decline after the previous surge. Thus, the Ministry of Health integrated the vaccine into childhood immunization to ensure households can access jabs at local Rwandan clinics without transportation costs.

 Experts say this will help reduce malaria cases in Rwanda, with improvements reported in mid-2026. In Rwanda, national childhood vaccination coverage is at 95%, yet gaps persist in reaching last-mile and hard-to-reach populations. Community Health Workers (CHWs) play a critical role in promoting and delivering vaccination services at the community level. This majority of vaccinated children reduces emergency appointments at clinics and financial strain on households.

GAVI and UNICEF’S Role

Since 2024, Gavi has played a significant role in the new malaria vaccination program in Rwanda. Gavi introduced the malaria vaccines RTS,S and R21/Matrix-M through procurement deals that enabled Rwanda to access affordable malaria vaccines while reducing hospitalizations. Gavi’s website stated that “[a]ccording to WHO estimates, the vaccine saves 1 life for every 200 children vaccinated.” Here, Gavi partnered with UNICEF to subsidize the entire cost, making the malaria vaccine free to every Rwandan child. Gavi financing the vaccine and UNICEF procuring it, with the Rwandan Ministry of Health delivering it through immunization, benefits every Rwandan citizen by protecting them from financial strain.

Vaccination Produces Widespread Economic Benefits

Recent results from the new malaria vaccination program in Rwanda show that it has directly reduced poverty across the country. The Rwandan government’s relationship with the organization Gavi has helped communities access life-changing protection that keeps children and adults safe while preventing families from extreme medical costs. This organization shows how international interventions can lift deprived countries out of poverty while strengthening national economic development.

– Alexandra Eaton

Alexandra is based in Birmingham, UK and focuses on Global Health for The Borgen Project.

Photo: Unsplash

September 2, 2026
https://borgenproject.org/wp-content/uploads/borgen-project-logo.svg 0 0 Jennifer Philipp https://borgenproject.org/wp-content/uploads/borgen-project-logo.svg Jennifer Philipp2026-09-02 03:00:292026-09-02 04:00:32Malaria Vaccination Program in Rwanda Helps Families in Poverty 
Global Poverty, Health, Mental Health

7 Facts About Mental Health in Guinea-Bissau

Mental Health in Guinea-BissauMental health is an essential part of overall health and well-being, yet many countries continue to face barriers to providing accessible mental health care. In Guinea-Bissau, limited specialist services and wider pressures on the country’s health system create challenges for mental health care. At the same time, international organizations and development programs are supporting health professionals and social services, creating opportunities to improve mental health in the country. 

7 Facts About Mental Health in Guinea-Bissau

  • No Stand-Alone Mental Health Policy or Law: Developing an effective mental health system often begins with clear national policies and legislation. The WHO Mental Health Atlas 2020 reports that Guinea-Bissau had no stand-alone mental health policy or plan and no stand-alone mental health law. The country also had no separate or integrated policy or plan specifically covering child or adolescent mental health. These gaps show the importance of continued policy development as the country works to strengthen its mental health system.
  • Mental Health and Psychosocial Support Training is Taking Place: Recent international programs have focused on strengthening the skills of professionals who support people experiencing mental health challenges. UNICEF reported that it worked with WHO and Interpeace in Guinea-Bissau to strengthen the knowledge and skills of health professionals and social service workers in mental health and psychosocial support. This included training social workers within the health sector, helping professionals provide better support to vulnerable children and families.
  • The Country Has a Limited Mental Health Workforce: Access to mental healthcare is an important part of improving mental health in Guinea-Bissau and depends not only on services but also on the professionals available to provide them. The WHO recorded 27 mental health professionals in Guinea-Bissau, including 16 mental health nurses, three psychologists, three social workers and five other specialized mental health workers. The Atlas also reports that there were no psychiatrists at the time of the assessment, highlighting the country’s limited specialist workforce. Efforts to strengthen the wider workforce continue. In 2025, the World Bank approved a $20 million Guinea-Bissau Human Capital Project to improve health, education and social protection services. The project includes capacity building for health professionals, teachers and social workers. Earlier efforts also focused directly on mental health, such as a public mental health program that trains general health workers to identify and manage mental health conditions.
  • Changing Weather Could Place Further Pressure on Mental Health: Mental health in Guinea-Bissau is also connected to wider social and environmental challenges. In a 2024 article, psychiatrist Dr. Carol Lim discussed the potential mental health effects of changing weather patterns in the country. She highlighted how poverty, illness, climate-related anxiety and possible migration could increase mental health challenges while placing additional pressure on Guinea-Bissau’s limited medical infrastructure. This shows how improving mental health services may become increasingly important as communities face the effects of environmental change.
  • Efforts are Underway to Integrate Mental Health into General Health Care: Primary health care can play an important role in expanding access to mental health support. Although the WHO Mental Health Atlas 2020 found that Guinea-Bissau had not achieved functional integration of mental health into primary healthcare under its assessment criteria, earlier initiatives attempted to address this challenge. A public mental health program described in “Psychological Medicine” trained general health workers to identify and manage mental health conditions, helping make mental health support available through professionals already working within the wider health system.
  • Most Mental Healthcare is Paid for Out of Pocket: The way health care is financed can influence people’s ability to obtain treatment. According to the WHO Mental Health Atlas 2020, people in Guinea-Bissau mostly or entirely paid out of pocket for mental health services and psychotropic medicines. The Atlas also reported that national health insurance or reimbursement schemes did not cover treatment for conditions including psychosis, bipolar disorder and depression. These financial barriers can make accessing mental healthcare particularly difficult for people with limited incomes.
  • International Cooperation is Supporting Mental Health Development: International cooperation is creating new opportunities to strengthen mental health in Guinea-Bissau. UNICEF has worked with WHO and Interpeace to strengthen mental health and psychosocial support skills among health professionals and social service workers. Guinea-Bissau is also included among the participating countries in the WHO African Region’s 2026 Mental Health Intercountry Learning Workshop for West and Central Africa. The workshop will allow participating countries to share experiences and develop roadmaps for strengthening their mental health systems.

Looking Ahead

Improving mental health in Guinea-Bissau will require continued investment in services, trained professionals and stronger health systems. Recent initiatives show that work is already taking place. UNICEF, WHO and Interpeace have supported mental health and psychosocial training, while the World Bank’s Human Capital Project is investing in the country’s health and social service workforce.

Guinea-Bissau’s participation in the WHO African Region’s 2026 Mental Health Intercountry Learning Workshop provides another opportunity for the country to learn from regional experiences and contribute to plans for strengthening mental health systems ahead of the region’s 2030 targets. Together, these initiatives could help expand the country’s capacity to respond to mental health needs over the coming years.

– Aniya Akram

Aniya is based in Bradford, UK and focuses on Global Health for The Borgen Project.

Photo: Wikimedia Commons

August 29, 2026
https://borgenproject.org/wp-content/uploads/borgen-project-logo.svg 0 0 Jennifer Philipp https://borgenproject.org/wp-content/uploads/borgen-project-logo.svg Jennifer Philipp2026-08-29 07:30:062026-08-29 02:24:597 Facts About Mental Health in Guinea-Bissau
Education, Global Poverty, Health

USAID Programs in Malawi

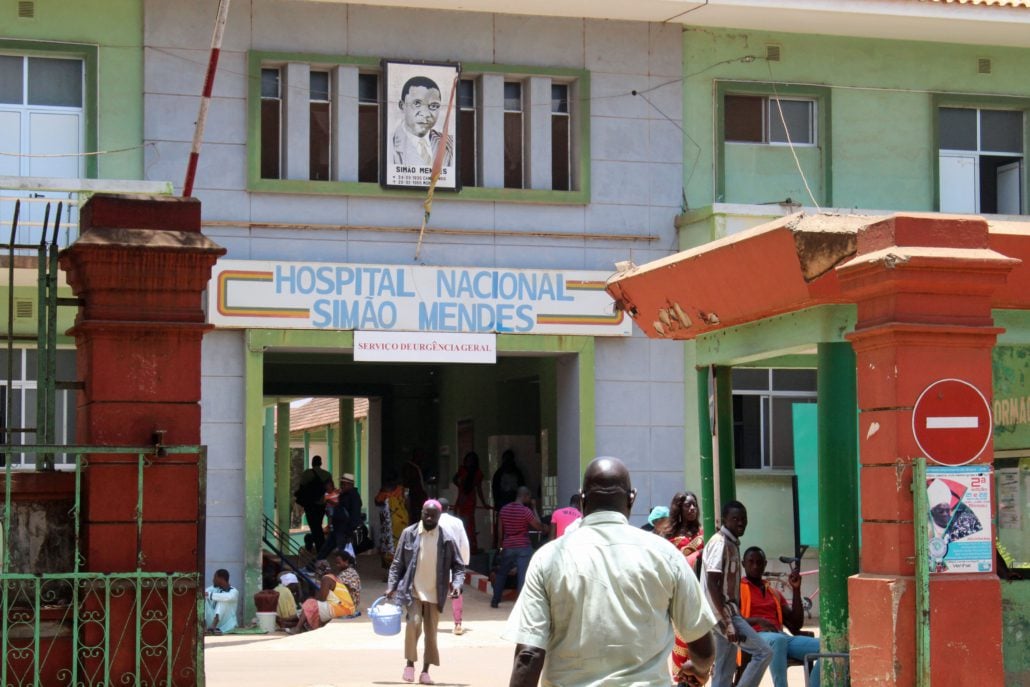
USAID Programs in MalawiMalawi, known as the Warm Heart of Africa, is home to several Bantu ethnic groups, including the Chewa, Lomwe, Yao, Ngoni and Tumbuka. Framed by Lake Malawi and the Great Rift Valley in Southeastern Africa, the country supports a population of 21 million people. World Bank demographic data indicates that 42% of citizens are less than 14 years old and more than 70% live below the national poverty line. For decades, USAID programs in Malawi provided critical support across health and education sectors. As a key bilateral partner, the foreign assistance agency backed healthcare initiatives through the U.S. President’s Emergency Plan for AIDS Relief (PEPFAR) starting in 2006. Twenty years later, Malawi is grappling with recent funding terminations: severe food insecurity due to climate shocks. Partners implementing PEPFAR, such as EGPAF Malawi and Partners in Hope, slashed an immediate 45% of HIV awards.

Shortcomings on Healthcare and Education

In both education and healthcare, Malawi faces severe resource and staffing shortages, that hinder long-term development and resilience. The nations’ physician density is only around 0.5 doctors per 10,000 patients. With similar underfunding issues, the educations sector closely mirrors these systemic healthcare challenges. Overcrowded classrooms and high student-to-teacher ratios leave schools ill-equipped to support young learners. In rural areas, teachers like Dinesi Namagowa emphasize this in times of disasters, when “learners can’t come to school. Classrooms, toilets, books and teaching materials are often destroyed.” Sometimes, classes are held under trees or inside leaking tents which accumulate into a national struggle with each storm and heavy rain. Returning to healthcare, the rate of new HIV infections is triple the world’s rate: 0.6 in Malawi compared to 0.2 globally, per 1,000 uninfected people, as of 2024.

Navigating Healthcare Transitions

Despite past achievements, recent global funding shifts and administrative adjustments required local healthcare providers to adapt rapidly. Historically, USAID programs in Malawi reached more than 700,000 citizens living with HIV/AIDS while expanding early grade literacy across rural schools. When budget reallocations impacted partner awards, regional health networks mobilized to safeguard these essential community services.

In a study of 72 Malawians, 78% of respondents reported significant currency depreciation and price spikes. Secondary data suggests that 435,000 Malawians could fall into extreme poverty linked to the suspension of aid.

In response, Malawian healthcare leaders and non-governmental partners decentralized care and integrated mobile clinic hubs to ensure uninterrupted treatment for vulnerable populations in rural districts and established new structural agreements.

Bilateral Agreements and Sustainable Solutions

In January 2026, the bilateral framework marked a major milestone by signing a $792 million Health Cooperation Memorandum of Understanding. This strategic arrangement commits $143.8 million annually over five years to combat HIV/AIDS, malaria and other infectious diseases.

Rather than relying solely on parallel donor delivery systems, this framework co-invests directly into Malawi’s domestic healthcare infrastructure. Local non-governmental organizations like Partners in Hope maintain frontline clinic operations to prevent treatment disruptions. Furthermore, community health networks deploying trained local advocates have successfully maintained treatment retention rates above 85% across target districts.

Fostering Long-Term Educational Progress

Educational development remains another vital area where partner support drives lasting change. Prior contributions to Malawi’s education sector generated hard-won gains for student scholarships, classroom construction and the distribution of Teaching and Learning Materials. UNICEF budget briefs highlight that maintaining continuous financial support for primary education shields young demographics from generational poverty risks and keeps children in school. Expanding this progress into secondary schools is an ideal next step for education development in Malawi.

Looking Ahead

By reinforcing community-led clinic operations and expanding sustainable co-investment models, USAID programs in Malawi continue empowering local institutions. Through strong bilateral collaboration and resilient local leadership, Malawi is establishing a durable foundation for long-term health, education and economic growth.

– Sila Elitok

Sila is based in Zurich, Switzerland and focuses on Politics for The Borgen Project.

Photo: Wikimedia Commons
August 29, 2026
https://borgenproject.org/wp-content/uploads/borgen-project-logo.svg 0 0 Jennifer Philipp https://borgenproject.org/wp-content/uploads/borgen-project-logo.svg Jennifer Philipp2026-08-29 01:30:102026-08-29 01:40:19USAID Programs in Malawi
Global Poverty, Health, HIV/AIDS

Addressing HIV/AIDS in Timor-Leste

HIV/AIDS in Timor-LesteAlthough HIV/AIDS in Timor-Leste remains relatively uncommon compared with many countries in the region, it remains an important public health concern. Timor-Leste has a low-level HIV epidemic, but new cases continue to be identified among the general population, including people attending antenatal, sexually transmitted infection and tuberculosis clinics. Limited access to HIV testing, stigma surrounding the disease and gaps in rural health care continue to challenge prevention and treatment efforts. While the country’s HIV epidemic remains relatively small, continued investment in prevention, education and treatment is essential to reducing new infections and improving long-term public health.

Timor-Leste Maintains a Low HIV Burden

Timor-Leste reported its first HIV case in 2003, shortly after gaining independence. Since then, the government has collaborated with international partners to strengthen HIV prevention, testing and treatment services. Although HIV/AIDS in Timor-Leste remains relatively uncommon, low HIV testing rates continue to limit early diagnosis, particularly in underserved communities. In remote areas, limited medical resources, shortages of trained health workers and long travel distances can delay testing and treatment, increasing the risk of undiagnosed infections.

Limited Access To Testing and Health Care Remains a Challenge

Several barriers continue to affect Timor-Leste’s HIV response. HIV-related stigma discourages some people from seeking testing or treatment because they fear discrimination from their families or communities. Limited health infrastructure outside the capital also makes it difficult for many people to access medical services. In addition, comprehensive sexual health education remains limited, leaving many young people without accurate information about HIV prevention. Together, these challenges highlight the importance of continued investment in public education, accessible health care and community awareness programs.

Despite these challenges, HIV testing services have reached thousands of people. In 2022, 10,913 people across five districts accessed HIV testing services and peer education on HIV prevention, testing and treatment. The country has also expanded efforts to improve access to HIV self-testing and pre-exposure prophylaxis (PrEP), with national guidelines developed to support these services. These efforts are important for increasing early diagnosis and connecting people who test positive with appropriate treatment and care.

In 2022, the Ministry of Health reported 250 new HIV cases, and 77 of those people had not yet started antiretroviral treatment, highlighting the continued gap between diagnosis and access to treatment.

HIV and Poverty Are Closely Connected

HIV/AIDS in Timor-Leste is not only a health issue but also a development challenge. Nearly 42% of people in Timor-Leste live below the national poverty line, making the cost of health-related services and prevention measures an important concern for vulnerable communities. In some areas, the cost of HIV prevention can create an additional barrier. For example, free condoms are distributed through a key-population organization in only five of Timor-Leste’s 13 municipalities, while people in other areas may have to pay around $2 for a pack of three condoms, a cost that some people cannot afford. For people living in poverty or in areas with limited health services, these financial and geographic barriers can make it more difficult to access HIV prevention, testing and treatment.

Government and International Partners Are Strengthening the Response

Timor-Leste’s Integrated National Strategic Plan for HIV, STIs and Viral Hepatitis (2022–2026) has strengthened the country’s response by bringing HIV, sexually transmitted infections and viral hepatitis into one coordinated framework. The Ministry of Health finalized and endorsed the plan, while it launched new national guidelines for eliminating mother-to-child transmission of HIV. The national response has also advanced HIV self-testing and pre-exposure prophylaxis (PrEP) through new guidelines and procedures, helping expand prevention and testing options for people at higher risk. Together, these measures support earlier diagnosis, stronger prevention and improved access to HIV services.

WHO has worked closely with Timor-Leste’s Ministry of Health to strengthen HIV services, including developing guidelines for antiretroviral treatment, HIV testing and the elimination of mother-to-child transmission. In January 2023, WHO and the Ministry of Health launched pilot projects for HIV self-testing and pre-exposure prophylaxis (PrEP) in Dili; nearly 1,000 HIV self-tests were made available and more than 200 people began PrEP. UNFPA has also supported the Ministry of Health’s HIV response, including a 2019 training that prepared 23 health workers on HIV testing, treatment, PrEP and PEP, prevention of mother-to-child transmission and HIV-related stigma. UNAIDS, through the UN Joint Team, has supported the national HIV response, including HIV testing, prevention education and the development of HIV self-testing and PrEP guidelines.

Continued Investment Is Key To Preventing New Infections

Timor-Leste has an opportunity to maintain its low HIV burden by continuing to invest in prevention, education and accessible health care. Expanding HIV testing, reducing stigma and strengthening health services in rural communities can help prevent new infections while improving the quality of life for people living with HIV. Continued collaboration between the government, local communities and international partners will not only strengthen Timor-Leste’s HIV response but also contribute to poverty reduction, healthier communities and sustainable development.

– Adebisi Aliyah Adeola

Adebisi is based in Cairo, Egypt and focuses on Global Health for The Borgen Project.

Photo: Wikimedia Commons

August 27, 2026
https://borgenproject.org/wp-content/uploads/borgen-project-logo.svg 0 0 Jennifer Philipp https://borgenproject.org/wp-content/uploads/borgen-project-logo.svg Jennifer Philipp2026-08-27 01:30:372026-08-27 01:31:32Addressing HIV/AIDS in Timor-Leste
Global Poverty, Health, Sustainable Development Goals

An Update on SDG 3 in Italy

SDG 3 in ItalyItaly has a population of 59,250,593 people throughout 7,896 municipalities. Italy demonstrates sound performance in health and wellbeing measures, evidenced by a score superior to the Organisation for Economic Co-operation and Development (OECD) average on seven out of 10 key indicators. The OECD is an intergovernmental organization that promotes policies to enhance global economic and social well-being.

Another key indicator of progress in Italy is a global ranking of 26 out of 169 countries in achieving Sustainable Development Goals (SDGs).

Despite Italy’s positive progress, poverty in Italy remains a concern which is important to understand in the context of SDGs. This is particularly so in relation to SDG 3, which aims to promote and improve population health and wellbeing. Here are some updates on SDG 3 in Italy.

Poverty in Italy

Poverty is a social issue in Italy, despite the country being one of Europe’s largest economies. The 2024-2025 report from Italy’s National Institute of Statistics states that more than 5.7 million people and 2.2 million households in Italy were living in poverty. These numbers amount to 9.8% of individuals and 8.4% of households respectively. These numbers remained largely consistent with the previous reporting year.

A rigorous effort to alleviate poverty in Italy is demonstrated through several means, including family allowances and benefits, funded childcare, income support, improved health care access, social services and regional development initiatives. For example, subsidized childcare and school meal assistance are available in some areas in Italy, greatly assisting households. Also, resources to alleviate poverty are dedicated to regions such as Calabria and Campania, where poverty and social exclusion rates are markedly high.

Italy’s National Institute of Statistics highlights the recent improvements from efforts to alleviate poverty. The number of people at risk of poverty or social exclusion fell from 23.1% in 2024 to 22.6% in 2025, household incomes increased and income inequality marginally decreased.

The Sustainable Development Goals (SDGs)

The SDGs comprise 17 global objectives, which the United Nations (UN) developed in 2015. The SDGs represent a crucial call for action by developed and developing countries in a global partnership. The UN developed a 15-year plan to 2030, namely, The UN 2030 Agenda for Sustainable Development. The SDGs were formed as key measurable targets alongside overarching goals to end poverty, protect the environment and ensure prosperity within countries.

As stated above, Italy places at 26 out of 169 countries in the SDG ranking and has an index score of 79.9.

Sustainable Development Goal 3

The overarching aim of SDG 3 is to promote and improve well-being and ensure healthy living for all individuals at every stage of life. SDG 3 comprises 17 sub-groups, all representing important determinants of health. In Italy, 13 out of 17 sub-groups are currently on track or maintaining SDG achievement, while four sub-groups are experiencing challenges, indicated by scores stagnating or tracking at less than 50% of the required rate. Italy’s current progress with SDG 3 is greatest within the sub-group, increased life expectancy at birth.&lt;/p&gt;<h2>How Italy is Addressing SDG 3

Addressing SDG 3 is crucial as health and wellbeing are cornerstones to attaining a better quality of life. This applies to individuals and the broader population. The National Strategy for Sustainable Development (NSSD) is embedded in Italy’s public health framework as a key mechanism to facilitate Italy’s progress with SDG3. The NSSD is a comprehensive agenda which aligns with the UN 2030 Agenda for Sustainable Development, thereby supporting the achievement of SDGs in the Italian socio-economic and political context.

The NSSD coordinates initiatives at local and national levels, with examples including, yet not limited to: Promoting partnerships between government and non-government organizations to expand health coverage, reforming and making healthcare more accessible via telemedicine services, increasing healthcare staffing and tackling gaps in life-expectancy between the northern and southern regions of Italy. Addressing gaps in life expectancy represents an important action, as this is an SDG 3 component currently tracking at less than 50% of the required rate.

Additionally, Italy works with the World Health Organization (WHO) through the Italian Health Equity Status Report Initiative, to identify and reduce disparities in health outcomes. Examples of dual efforts between Italy and WHO to address SDG 3 include expanding home care services, telemedicine and improved access to childcare and education services, with a particular focus on disadvantaged populations.

Expanding the provision of home care and telemedicine are key public health goals in Italy and central components of Italy’s National Recovery and Resilience Plan (NRRP). As well, applying efforts to improve these areas of health are important to reduce fragmentation between healthcare services, thus improving continuity of care, reducing pressure on the hospital system and improving health care access for the Italian population.

Healthcare Access: Challenges and Progress

The European Environment Agency states that Italy is making significant progress with the SDGs, but continues to experience many challenges. Socioeconomic challenges are notable, including a widening generational economic gap, poor social mobility and enduring poverty which impacts the health and wellbeing of numerous individuals and households.

Poverty is a key factor which can affect progress with SDG 3 in Italy, as individuals affected by poverty are more likely to face barriers that negatively impact their health status. For example, poverty is a barrier to affording health care services, medications and health insurance. Added to this, regions experiencing poverty are more likely to be in areas where healthcare facilities are scarce or hard to access. Considering this, efforts to improve healthcare access, such as telemedicine, are particularly important. Out-of-pocket healthcare spending remains relatively high in Italy and this can place a burden on lower-income households. Considering the above, strengthening access to and affordability of healthcare in Italy are important steps to improving the health of the wider Italian population, regardless of income or location.

Conclusion

In summary, the current update on SDG 3 in Italy is optimistic, as evidenced by 76.5% of SDG 3 subgroups marked as green and on track, a country ranking of 26 out of 169 and an index score of 79.9 in the UN 2030 Agenda for Sustainable Development. SDG 3 encompasses a wide range of health and wellbeing domains and numerous and concurrent initiatives match this, namely, the NSSD, Italian Health Equity Status Report Initiative and Italy’s NRRP. Persistence of initiatives targeted towards strengthening healthcare access and affordability are crucial in enabling further progression with SDG 3. This will ensure that Italy will be able to address the key barriers that people experiencing poverty face and improve healthcare access for the overall population. It is anticipated that continued efforts will ensure a greater proportion of Italian people are able to experience improved health and wellbeing outcomes.

– Alexandra Nash

Alexandra is based in Belfast, UK and focuses on Good News and Global Health for The Borgen Project.

Photo: Unsplash

August 19, 2026
https://borgenproject.org/wp-content/uploads/borgen-project-logo.svg 0 0 Jennifer Philipp https://borgenproject.org/wp-content/uploads/borgen-project-logo.svg Jennifer Philipp2026-08-19 01:30:452026-08-18 14:06:03An Update on SDG 3 in Italy
Global Poverty, Health, Women & Children

The Immediate Crisis of Maternal Care in Bangladesh

Maternal Care in BangladeshBangladesh is encountering significant obstacles in maternal and infant care, according to new documents that the United Nations Inter-Agency Group for Child Mortality Estimation released. Progress has been made since 1990, but Bangladesh still has one of the highest rates of stillbirths in South Asia, requiring urgent intervention.

Factors Leading to Maternal Death 

Postpartum hemorrhage is the leading cause of maternal death in Bangladesh, accounting for approximately 40% of maternal deaths. Eclampsia is the second-leading cause, responsible for about 23% of maternal deaths. Severe anemia also contributes to maternal mortality, although it is not the third-leading cause of death in the nationally representative survey.

Studies show that many women who died from postpartum hemorrhage were unable to receive timely, appropriate care because of delays in treatment, limited maternal healthcare resources and overburdened health facilities. In one study, two of 11 women who experienced postpartum hemorrhage died at home, while 12 of 24 women died in public health facilities. Two of 12 women died while being transported to a health facility, and one of six died at a private facility.

Maternal Child Health Handbook

The World Health Organization proposed a home-based maternal record as an efficient tool to effectively connect pregnant women and their families to community health employees and specialists. The maternal and child health handbook (MCH) is the most extensive home-based book that comprises all the records of the continuous care for both mothers and children. The MCH includes labor and postpartum care. The MCH communication intervention was utilized on a mobile platform, which included text, audio messages and phone calls if vital. The intervention included sending reminders for antenatal care visits and a list of locations for proficient birth specialists.

Accessibility to Education

Improving access to maternal health care and skilled birth attendants is essential to reducing maternal mortality, particularly by ensuring women receive timely care during pregnancy, childbirth and postpartum emergencies. Education can also play an important role in helping women recognize health risks and seek appropriate care. Mothers in Bangladesh now have access to the Joint Action for Nutrition Outcome. It is a CARE project that’s financed by the European Union and Austrian Development Cooperation. Women get to learn how to take precise safety measures, get doctor checkups and eat nutritious meals.

United Nations Population Fund Deployment of Midwives

The United Nations Population Fund (UNFPA) stationed midwives in government facilities in Bangladesh and implemented three-year specialized midwifery courses in 2012. Midwives are trained health professionals who provide sexual, reproductive and maternal health care and can help women receive timely care during pregnancy, childbirth and postpartum emergencies. In June 2018, 593 midwives were deployed, and in August 2018, another 550 midwives were placed at various Upazila medical centers in Bangladesh. These successful midwives, such as Tania Aktar, who delivered 200 babies, provided prenatal care to thousands of women. The UNFPA’s incorporation of midwives into healthcare systems will help Bangladesh accomplish a zero maternal mortality rate.

Bangladesh: Poverty and Maternity Care

Many families in Bangladesh continue to live in extreme poverty, making it difficult for pregnant women to access the nutritious food they need for a healthy pregnancy. In one study, women reported eating less during pregnancy because they could not afford staple foods such as rice and potatoes or other nutritious foods. Some families survived by relying on neighbors for small amounts of rice, which they sometimes sold to purchase other necessities such as salt and vegetables. When household incomes were insufficient, some pregnant women also took on physically demanding work, including cleaning other people’s homes, to help support their families. These financial hardships contribute to poor maternal nutrition and increase the risk of complications during pregnancy and childbirth.

Looking Ahead

Addressing the crisis of maternal care in Bangladesh requires women to utilize child health handbooks to be able to communicate with medical professionals. Bangladesh has enlarged their midwife deployment in government facilities to enhance accessibility to proficient care and improve educational initiatives.

– Ruba Alghurab

Ruba Alghurab is based in Debary, FL, USA and focuses on Good News for The Borgen Project.

Photo: Pexels

August 10, 2026
https://borgenproject.org/wp-content/uploads/borgen-project-logo.svg 0 0 Jennifer Philipp https://borgenproject.org/wp-content/uploads/borgen-project-logo.svg Jennifer Philipp2026-08-10 03:00:102026-08-19 22:37:46The Immediate Crisis of Maternal Care in Bangladesh
Global Poverty, Health, USAID

USAID Programs in Kazakhstan

USAID Programs in KazakhstanUSAID, or the United States Agency for International Development, is a U.S. government agency that administers foreign development and humanitarian assistance. Its funding policy is aligned with U.S. foreign policy objectives. USAID began operations in Kazakhstan when it broke off from the Soviet Union in 1991. USAID’s core activities are global development assistance, global health, humanitarian assistance and economic development, among other priorities. Following the USSR’s disintegration in 1991, USAID began operations supporting development, as mentioned above.

While USAID programs in Kazakhstan contributed to development efforts, broader issues relating to socio-economic indicators continue. According to the World Bank, about 0.04% of Kazakhstan’s population lives below the international poverty line of $3 a day. Indicating a relatively low poverty rate. However, the same World Bank report states that in Financial Year 2027, Kazakhstan’s growth rate would moderate from 6.5% last fiscal year to 4.6%. Meanwhile, Kazinform reports that while Kazakhstan spends about $15 billion or 7 trillion Kazakh Tenge on education, about 73.5% of the expenditure goes to salaries and social payments. These indicators highlight areas that continue to shape the country’s various economic indicators.

Key USAID Programs in Kazakhstan

Here are the key areas where USAID focuses its programs:

  1. Economic Development: USAID provided $39 million in funding for the Power Central Asia program to decarbonize and introduce renewable energy in the country’s energy sector. Emin Hassan’s article provides evidence for this investment. In the article, Mr. Emin talks of how wind energy has one of the highest potentials for renewable expansion, due to Kazakhstan’s arid and windy climate. According to USAID, the agency supported initiatives through the New Silk Road Initiative to diversify the country’s economy and strengthen regional growth.
  2. Rule of Law: Kazakhstan is often considered an “authoritarian, super-presidential” country, where the Kazakh president has sweeping powers; international organizations have reported restrictions on civil liberties and press freedoms. According to USAID, it conducts programs such as projects supporting legal reform, nonprofit advocacy and the independence and professionalism of the Kazakh judiciary. One of those programs was Kazakhstan’s Rule of Law program which receives funding and support from both USAID and the European Union. One of the many objectives included: improving the legal climate for businesses, the legal framework for Civil Society Organizations and Judicial independence and modernization, according to the American Bar Association (ABA). As the Astana Times reported, due to the implementation of this program, Kazakhstan’s overall score at the WJP Rule of Law improved to 0.54. Additional improvements included the expansion of e – Justice systems, regulatory enforcement and anti-corruption frameworks improved, thus showing notable positive movement in the “absence of corruption” and “order and security” subsections of the ranking.
  3. Civil Society and Human Rights Programs: USAID in Kazakhstan has launched multiple programs in Kazakhstan, including the Civil Society Support Program in Central Asia (CSSP) and the Kazakhstan Human Rights Activity. These programs support citizen government initiatives and fund local NGOs. As fundsforNGOs and the U.S. Embassy in Kazakhstan reported, these programs’ accomplishments include $2,000-$10,000 grants to local civil society organizations and NGOs; funding for high-profile public events such as Almaty’s first “Trash Fleet;” the brokering of partnerships between academics, civic activists and local businesses; and finally, the provision of specialized capacity-building courses for regional civil society leaders.

USAID’s activities in Kazakhstan are part of a broader U.S. – Kazakhstan development cooperation.

The Impact

USAID’s activities in Kazakhstan affect several sectors, including:

  1. Public Health: According to the Joint United Nations Program on HIV/AIDS, USAID programs helped combat HIV cases through a massive increase in HIV/AIDS testing and an increase in outreach programs. USAID launched the Central Asia HIV Flagship program to strengthen HIV prevention, testing and treatment in Kazakhstan and the wider Central Asian region. Its objective is to reduce HIV incidence and deaths. Its main group included gay men, sex workers and drug abusers. As of 2020, the program has tested more than 10,000 people through many flagship initiatives, provided life – saving care and support services for more than 3,000 people infected by HIV and upgraded 15 different AIDS centers in Kazakhstan. Recent cuts to these programs put these initiatives at risk of cancellation. UNAIDS reported a 90% reduction in testing.
  2. Civil Society and Media: The Diplomat reported that recent cuts to USAID have put training programs and support for independent media at risk because the funding cuts could force organizations to suspend them.
  3. Economy and Trade: The USAID Power Central Asia regional center has supported diversifying the country’s economy, easing supply chain bottlenecks and mitigating the effects of the war in Ukraine.
  4. Energy and Climate: As the U.S. Embassy in Kazakhstan and Power Central Asia reported, USAID facilitated and funded multiple energy programs in the country, supporting Kazakhstan’s transition to renewable energy. According to USAID, its accomplishments extended to the provision of 1790 MW of renewable energy, the reduction or avoidance of 18 million tons of CO2, $3 billion USD in investments and 2,194 people trained in the Central Asian energy sector.

Challenges That USAID in Kazakhstan Faces

Here are the challenges the organization has faced while operating in Kazakhstan:

    1. Challenges With Operating or Maintaining Programs: Recent funding cuts have hurt operations, sometimes even complete elimination of programs, and delayed expansion in Kazakhstan.
    2. Harm to Publish Health Programs: The same funding cuts have also hurt USAID-sponsored HIV/AIDS testing and other public health initiatives. This has put large parts of the population at higher risk of HIV/AIDS and tuberculosis, due to low testing and medical outreach.
    3. Censorship: Due to the funding cuts, local NGOs had to censor themselves or cease operations entirely due to operational bans by the Kazakh government. This has fueled public petitions directed towards USAID and the U.S. government due to the inclusion of foreign funding restriction laws and funding cuts.
    4. Restrictions from the Government: The restrictive nature of the Kazakh government has also hampered operations due to the restrictions they place on foreign-funded NGOs operating in the country. This includes mandatory reporting to the state; the NGO needs to list itself on the National registry, including disclosing names and registration numbers.

The Future of USAID in Kazakhstan

Foreign policy priorities will influence the future of USAID in Kazakhstan, congressional appropriations and decisions that the presidential administration made. Recent policy changes have altered funding priorities for some international assistance programs.

– Dhruv Bandhu

Dhruv is based in Bengaluru, Karnataka, India and focuses on Technology and Politics for The Borgen Project.

Photo: Wikimedia Commons
August 9, 2026
https://borgenproject.org/wp-content/uploads/borgen-project-logo.svg 0 0 Jennifer Philipp https://borgenproject.org/wp-content/uploads/borgen-project-logo.svg Jennifer Philipp2026-08-09 01:30:032026-08-09 00:53:38USAID Programs in Kazakhstan
Disease, Global Poverty, Health

Diseases Impacting Venezuela

Diseases Impacting VenezuelaOutbreaks of infectious diseases are the primary health challenges impacting the population and shelter infrastructure in Venezuela. A June 24, 2026, 7.2 magnitude earthquake along Venezuela’s northern coast affected people significantly, along with a subsequent 7.5 magnitude earthquake that killed 32 people, injured 700 people and devastated areas as distant as La Guaira state 160 km east. The earthquakes impacted 1.7 million buildings resulting in widespread power outages across several states.

Of Venezuela’s 31.7 million population, 20 million (63.1%) already lived in poverty, population susceptibility to contracting infectious diseases was high due to no government epidemiological bulletin publications since 2016 and early economic loss predictions outlines costs of 7% of Venezuela’s $111 billion GDP. Structural losses immediately exacerbated the issue of infectious diseases impacting Venezuelan earthquake victims through eliminating their access to water, sanitation and hygiene (WASH) facilities, healthcare workers, hospitals, adequate medical care and nutritious food. Increasing earthquake victims’ susceptibility to infectious diseases such as measles, dengue and yellow fever, malaria, diarrhea and skin infections.

Concerns

  • Infectious Disease Treatment Challenges: Medical care services have been sparse due to the impact of the earthquakes on regional healthcare facilities and the fact that they were already 37% short of essential medicines following years of poor economic investment. A Pan-American Healthcare Association (PAHO) analysis showed that more than 50 hospitals in seven states are still functioning but that many facilities experienced critical structural damage. Additionally, the earthquakes resulted in the evacuation of three hospitals, the damaging of 20 primary care units and overcrowding in healthcare facilities. Corpse remains have also led to disease outbreaks and contamination risks.
  • Rising Fatality and Victim Rates: The Los Angeles (LA) Times reported that Venezuela’s health system, which was already weakened by an eight-year economic depression leading to the departure of more than half of the nation’s doctors and other skilled health professionals, had, by July 11, 2026, helped elevate the earthquake’s death toll to 3,800, with 16,700 people injured.
  • Infrastructure Damage: The earthquake destruction zone now presents economic challenges at an estimated $37 billion in losses, including $24 billion in housing and healthcare damage, $13 billion worth of mostly road and energy generation infrastructure damage, meaning 650,000 people will need humanitarian assistance with approximately 17,000 left homeless. Economic disruption means costs will rise further and shelter and healthcare reconstruction efforts become heavily constrained by a pre-existing weak economy.

Solutions

  • Imminent Infectious Disease Treatment: UN subsidiaries have sent 68 tonnes of medical, WASH and household supplies, alongside contributing primary healthcare services through distributing hygiene kits and further sanitation infrastructure fueled by $306 million worth of funding from The Humanitarian Response Plan for Venezuela and private-sector donations.
  • Managing Fatality and Victim Rates: PAHO has presently recovered 6,400 people by concentrating on early recovery, mobilizing emergency specialist expertise, providing health services such as sanitary post-mortem care, diagnostic imaging and immunizations, alongside pleas for a $24 million emergency fund to enable epidemiological surveillance in the earthquake destruction zone.
  • Remedying Regional Infrastructure Damage: La Guaira state sport complexes are providing their facilities as temporary logistics hubs for the storing of health, water and food aid. Their athletic facilities also offer shelter for thousands of displaced people. The United Nations High Commissioner for Refugees (UNHCR) is trying to sustain infrastructure advancements, “seeking $14.85 million to support up to 30, 000 people with shelter and essential aid over the next six months.”

Looking Ahead

June 2026 publications painted a grave picture of what presently, and in the future lay ahead for Venezuela, its pre-earthquake impoverished population of 20 million and its healthcare services. Earthquake destruction zone infectious disease challenges clearly reside, yet by both national and international aid recognizing this issue, prompt economic, shelter and medical relief has advanced future stability against the multitude of current factors that encourage the problem of infectious diseases impacting Venezuela. 

– Oliver Jones

Oliver is based in Cheshire, UK and focuses on Business and Global Health for The Borgen Project.

Photo: Flickr

August 2, 2026
https://borgenproject.org/wp-content/uploads/borgen-project-logo.svg 0 0 Jennifer Philipp https://borgenproject.org/wp-content/uploads/borgen-project-logo.svg Jennifer Philipp2026-08-02 07:30:322026-07-31 23:49:53Diseases Impacting Venezuela
Page 3 of 216‹12345›»

Get Smarter

  • Global Poverty 101
  • Global Poverty… The Good News
  • Global Poverty & U.S. Jobs
  • Global Poverty and National Security
  • Innovative Solutions to Poverty
  • Global Poverty & Aid FAQ’s
Search Search

Take Action

  • Contact Your Leader
  • Donate
  • 30 Ways to Help
  • Volunteer Ops
  • Internships
  • Courses & Certificates
  • The Podcast
Borgen Project

“The Borgen Project is an incredible nonprofit organization that is addressing poverty and hunger and working towards ending them.”

-The Huffington Post

Inside The Borgen Project

  • Contact
  • About
  • Financials
  • President
  • Board of Directors
  • Board of Advisors

Get Smarter

  • Global Poverty 101
  • Global Poverty… The Good News
  • Global Poverty & U.S. Jobs
  • Global Poverty and National Security
  • Innovative Solutions to Poverty
  • Global Poverty & Aid FAQ’s

Ways to Help

  • Contact Your Leader
  • Donate
  • 30 Ways to Help
  • Volunteer Ops
  • Internships
  • Courses & Certificates
  • The Podcast
Scroll to top Scroll to top Scroll to top



