• Link to X
  • Link to Facebook
  • Link to Instagram
  • Link to TikTok
  • Link to Youtube
  • About
    • About Us
      • President
      • Board of Directors
      • Board of Advisors
      • Financials
      • Our Methodology
      • Success Tracker
      • Contact
  • Act Now
    • 30 Ways to Help
      • Contact Your Leader
      • Volunteer
      • Courses & Certificates
      • Be a Donor
    • Internships
      • In-Office Internships
      • Remote Internships
    • Legislation
      • Politics 101
  • The Blog
  • The Podcast
  • Magazine
  • Donate
  • Click to open the search input field Click to open the search input field Search
  • Menu Menu

Archive for category: Disease

Information and news about disease category

Disease, Global Poverty, Health

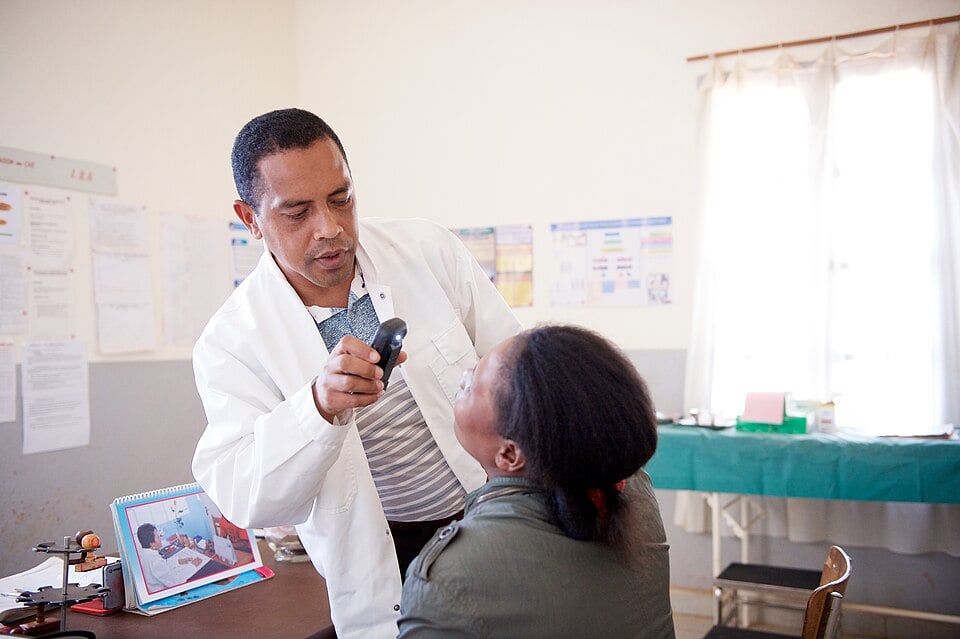
Malaria Education in Madagascar

Malaria Education in Madagascar
Madagascar, an island country east of Mozambique, faces significant poverty and malaria challenges. According to World Bank estimates, 69.2% of its population lived below the international $3-a-day poverty line in 2021, measured in 2021 purchasing-power-parity dollars. Malaria outbreaks have placed additional pressure on communities and health services.

What Works and What Does Not in the Current System?

Geography is crucial when discussing the incidence of malaria infection and why it is harder to contain in Madagascar than in other places with high malaria incidences. Madagascar is an island country heavily impacted by weather events such as cyclones and droughts. Its landscape includes both endemic lowlands and epidemic-prone highlands that create transmission zones, making it very hard to monitor and control the disease. This leads to the necessity of personalized or regionally specific prevention techniques, like malaria education in Madagascar alongside the use of ITNs and residual spraying.

WHO reporting identifies Madagascar as a malaria-endemic country where malaria cases increased markedly in 2024. The risk of malaria differs across communities and transmission settings. The implementation of the highly effective insecticide-treated nets (ITNs), indoor residual spraying (IRS), and seasonal malaria chemoprevention (SMC) have been in effect since the early 2000s and continue to be some of the most useful methods of preventing the disease. Although the CDC notes that indoor spraying lasts about three to six months and does not prevent people from being bitten, it simply kills mosquitoes that land on the sprayed surface.

Malaria-specific social and behavior change communication encourages the use of proven prevention methods, including insecticide-treated nets and indoor residual spraying. Community health workers can explain how to use these interventions and when to seek diagnosis and treatment. Another program for malaria control came from the ACCESS Program and the Ministry of Public Health and National Malaria Control Program partnering to create a community-centered program involving community health volunteers. This program included home visits for early detection and pre-referral treatment for severe malaria in children under five. By the end of ACCESS in 2025, nearly 14,000 community health volunteers were actively delivering malaria prevention and treatment services. ACCESS reports that more than 180,000 people received integrated community services in 2023-2024.

Time to Add Something New?

Although these programs extend prevention and treatment services, malaria remains a serious public health challenge in Madagascar. While the connection to community health volunteers has helped, and there has been some form of malaria prevention education through social and behavior change communication, the programs in place revolving around educating people on general malaria prevention and treatment methods in Madagascar need more investment to reach all villages across the country’s landscape.

A study done in Burkina Faso and Cote d’Ivoire by The Lancet Global Health found that pairing malaria education with the use of ITNs cut disease risk as much as indoor spraying combined with insecticide nets. The research showed a 22% reduction in cases in the following 10 months compared to just using nets alone. This evidence suggests malaria education in Madagascar could help reduce malaria alongside the use of insecticide nets and residual spraying. These findings suggest that targeted malaria education could complement nets, spraying, diagnosis and treatment in Madagascar, although this study in Madagascar has not demonstrated the same result.

Looking Ahead

Strengthening locally appropriate malaria education through community health workers and social and behavior change communication may complement existing prevention, diagnosis and treatment efforts. Reaching remote communities remains essential.

– Lily K. Gibson

Lily is based in Connecticut, USA and focuses on Global Health and Politics for The Borgen Project.

Photo: Wikimedia Commons

October 17, 2026
https://borgenproject.org/wp-content/uploads/borgen-project-logo.svg 0 0 Lynsey Alexander https://borgenproject.org/wp-content/uploads/borgen-project-logo.svg Lynsey Alexander2026-10-17 07:30:422026-10-16 10:20:34Malaria Education in Madagascar
Disease, Global Poverty, Technology

Tracking Ebola in the DRC With Mobile Phone Data

Ebola in the DRC
On May 15, 2026, the Democratic Republic of the Congo (DRC) declared its 17th Ebola outbreak since 1976. Two days later, the World Health Organization (WHO) determined that the Bundibugyo virus outbreak constituted a Public Health Emergency of International Concern. There is no licensed vaccine or specific treatment for this strain.

The virus spread fast. It passed 1,000 confirmed cases within 40 days. The 2018 outbreak in the DRC took about 235 days to reach that mark. As of Sept. 23, the DRC had reported 7,890 confirmed cases and 3,799 deaths across seven provinces, a crude case fatality ratio of 48.1%. For comparison, WHO says past Bundibugyo outbreaks had fatality rates between 30% and 50%. Numbers like these push health workers to find new ways to track Ebola in the DRC before it spreads further.

A Response Under Strain

The response to Ebola in the DRC has struggled to keep up. One month in, Médecins Sans Frontières warned that gaps in testing, contact tracing and community outreach were letting the virus outrun the response. By the two-month mark, confirmed cases had tripled. In just five weeks, they went from around 650 to more than 2,000. Deaths rose even faster, from 130 to over 700 in the same period. Trish Newport of Médecins Sans Frontières said teams were still chasing the outbreak instead of staying ahead of it.

Tracking Movement by Phone

A Swedish nonprofit called Flowminder is trying something different. It works with Vodacom, the DRC’s largest operator, with more than 26 million active subscriptions and nearly 35% of the market. Flowminder studies phone records created when phones connect to cell towers. The data are aggregated and anonymized, so no individual caller is identified. By tracking movement between areas over time, researchers can see where people travel. Linus Bengtsson, founder of Flowminder, told Reuters that knowing how people move offers clues about how infected people might move.

Flowminder published its first report on May 28 and updated it on June 4. Using anonymized Vodacom data, it ranked the health zones receiving the most travelers from Bunia, Mongbwalu and Rwampara, the outbreak’s first hotspots. By June 1, eight of the top 10 recipient zones already had confirmed cases. By the end of June, all 10 did.

The tool does not predict where an infected person will turn up. It flags which areas face a higher risk of importing the virus, so teams know where to look first. Kisangani shows how this works. The major river port does not border the affected areas. Even so, Flowminder’s first report listed it as the top destination in Tshopo province for travelers from the hotspots. Dr. Olivier le Polain, who leads epidemiology and analytics for WHO’s response, told Reuters the data showed significant risk there by mid-June. He said operations were strengthened before the first cases were detected. Those cases were confirmed in early July.

A Heavy Price for Children

Children in affected areas face particular risks. UNICEF estimates nearly 3 million children in affected areas face rising danger. By late June, more than 130 children in Ituri province had already lost a parent to Ebola in the DRC. UNICEF is seeking $70.7 million for its six-month response. As of the appeal, $20 million of that remained unfunded.

A Model Worth Building On

The system has limits. It only captures subscribers on the participating network, so people using other providers stay invisible. So do people who cross into nearby countries. The data are also aggregated and anonymized, which protects privacy but limits detail. That is why mobility data complement epidemiological surveillance rather than replace it. Testing, contact tracing and community work still do the core job. Flowminder and U.N. officials are working to bring other operators on board, which would sharpen the picture.

If that expansion succeeds, the same tool now helping track Ebola in the DRC could become a model for other outbreaks. It would fit anywhere health systems are stretched thin but phones are common. The DRC has faced this virus 17 times since 1976. Mobility data can help responders identify areas at higher risk earlier, complementing testing, contact tracing and community-based surveillance.

– Juan Guillermo Rueda Castrillón

Juan is based in Barcelona, Catalunya, Spain and focuses on Technology and Solutions, and Global Health for The Borgen Project.

Photo: Flickr

October 9, 2026
https://borgenproject.org/wp-content/uploads/borgen-project-logo.svg 0 0 Lynsey Alexander https://borgenproject.org/wp-content/uploads/borgen-project-logo.svg Lynsey Alexander2026-10-09 07:30:362026-10-08 08:03:47Tracking Ebola in the DRC With Mobile Phone Data
Disease, Global Poverty, Health

Ovarian Cancer Gaps in LMICs

Ovarian Cancer in LMICs
On May 8, 2026, people around the world marked World Ovarian Cancer Day, an annual campaign focused on raising awareness of ovarian cancer. Unfortunately, there are low rates of awareness of ovarian cancer in LMICs, otherwise known as low and middle income countries, making this campaign particularly important.

Ovarian Cancer Awareness

Ovarian cancer poses a significant threat as a gynecological cancer, with many cases diagnosed late due to vague symptoms such as bloating and difficulty eating. These symptoms are often mistaken for other conditions. The day unites health care professionals, advocacy groups, survivors and communities to promote education and fundraising.

#NoWomanLeftBehind Theme

The 2026 theme, #NoWomanLeftBehind, differed from previous years. According to the World Ovarian Cancer Coalition, fewer than 20% of women receive a stage I diagnosis, even in high-income countries like the United Kingdom and the United States. Outcomes and access to recommended treatment vary significantly between countries. This theme emphasizes equitable ovarian cancer outcomes, regardless of location or socioeconomic status.

Global Health Issue

Ovarian cancer remains a major global health issue. About seven in 10 women diagnosed with ovarian cancer die within five years, the highest death-to-diagnosis ratio among the four major women’s cancers. Global cases may rise by 53% by 2050. In lower-middle-income countries, cases are projected to rise by 82%, while cases in low-income countries are projected to rise by 151%.

World Ovarian Cancer Day

In response, leaders from ovarian cancer advocacy organizations worldwide established World Ovarian Cancer Day in 2013. The World Ovarian Cancer Coalition now leads the annual initiative, collaborating with more than 200 partner organizations, from grassroots patient advocacy groups to national health organizations, to promote earlier diagnosis and equitable access to care for women globally.

#ReachForTheScars Campaign

As part of the #NoWomanLeftBehind theme, the World Ovarian Cancer Coalition promoted the #ReachForTheScars campaign. This campaign highlighted the real experiences of women with ovarian cancer, generating 58 million impressions, reaching 164 countries and receiving more than 47,000 social engagements. Global partners, including the World Economic Forum, Union for International Cancer Control and Zentalis, also helped increase visibility. These figures demonstrate the campaign’s global reach and engagement.

The 2018 “Every Woman Study” Findings

In 2018, the World Ovarian Cancer Coalition conducted the Every Woman Study. The goal was to address the evidence gap and identify ways to improve survival and quality of life for women with ovarian cancer. With more than 1,531 women in 44 countries participating, it was the largest-ever global survey of women with ovarian cancer at the time.

The study showed more than two-thirds of respondents had never heard of ovarian cancer or knew little about it before diagnosis, and about nine in 10 respondents experienced multiple symptoms before receiving a diagnosis.

Additionally, access to genetic testing varied dramatically by country, with more than 80% of women who had two or more relatives with ovarian cancer not receiving genetic testing before their diagnosis.

The Every Woman Study – LMIC Edition

Following the 2018 results and the expected rise in ovarian cancer cases, the Every Woman Study: Low- and Middle-Income Edition launched in August 2021. It was a joint initiative between the World Ovarian Cancer Coalition and the International Gynecologic Cancer Society. The goal was to document the experiences of women with ovarian cancer in LMICs on a large scale.

Believing that the original 2018 study was not representative enough of lower-income countries, research was conducted on 2,446 participants across 22 LMICs, including regions such as South Africa, India and Jamaica. Participation occurred through interviews and surveys, with results examining factors like knowledge of ovarian cancer, route to diagnosis, treatment, financial impact and emotional support.

Finally completed in 2025, the study found that only about one in four women had heard of ovarian cancer and knew something about it before diagnosis. Additionally, around three in four women said that ovarian cancer affected their family’s finances, with 29.4% stating that their household income fell below what they needed to live on.

Access to genetic testing and advanced treatments like PARP inhibitors was also limited among participants. Furthermore, one in three women reported traveling more than two hours to reach their treatment center, illustrating yet another barrier to accessing treatment.

Next Steps

The Every Woman Study shows that closing ovarian cancer gaps requires more than awareness alone. Better access to diagnosis, treatment, genetic testing and support is essential, especially in LMICs. As World Ovarian Cancer Day continues to bring global attention to these disparities, its 2026 message, #NoWomanLeftBehind, serves as a reminder that every woman deserves a chance at better care, no matter where she lives.

– Diya Rajkumar

Diya is based in Redmond, Washington, USA and focuses on Good News and Global Health for The Borgen Project.

Photo: Flickr

October 9, 2026
https://borgenproject.org/wp-content/uploads/borgen-project-logo.svg 0 0 Lynsey Alexander https://borgenproject.org/wp-content/uploads/borgen-project-logo.svg Lynsey Alexander2026-10-09 01:30:312026-10-08 07:06:09Ovarian Cancer Gaps in LMICs
Disease, Global Poverty, Health

The Fight Against Tuberculosis in Timor-Leste

Tuberculosis in Timor-Leste
To much of the developed world, tuberculosis may seem like a distant threat. In 2024, however, the World Health Organization (WHO) estimated that 10.7 million people developed TB worldwide and 1.23 million died from the disease. The WHO South-East Asia Region accounted for 34% of global TB cases, making it central to efforts to reduce the disease burden. Recently, efforts have increased to combat tuberculosis worldwide.

Why Tuberculosis in Timor-Leste is So Prevalent

The circumstances facing this small Southeast Asian nation demonstrate the challenges surrounding tuberculosis in Timor-Leste.

Timor-Leste is a small, ethnically diverse country on the Malay Archipelago, about 400 kilometers north of Australia. Following the 1999 referendum that began its transition from Indonesian rule, Timor-Leste has struggled with extreme poverty, with an estimated 44% of the population living on less than three dollars a day.

When a person becomes seriously ill in Timor-Leste, location and income limit options. About 70% of the population lives in rural areas. That means in order to get to a hospital, a would-be patient must make a journey of several hours, most likely on foot. With a lack of paved roads and a steep, mountainous environment, travel can be taxing. Accounting for the intense heat of the dry season and the flash floods of the rainy season, the trip becomes almost impossible for an ill person to endure. For many Timor-Leste citizens, reaching a hospital when illness strikes is not a realistic option. These barriers help explain why access to tuberculosis diagnosis and treatment remains challenging in Timor-Leste.

Efforts to Address Health Care Access in Timor-Leste

Since the pandemic, a time when many nations became attuned to the state of their health care systems, some organizations implemented efforts to fix this issue in Timor-Leste. In 2020, for example, the IOM—a branch of the UN’s migration offices—developed a program to train health care workers in Timor-Leste to use new diagnostic technologies. The program aimed to strengthen tuberculosis diagnosis and build the skills of health care workers in Timor-Leste. In 2024, IOM reported its successes: they had trained six radiographers, 60 medical doctors, and three laboratory technicians to detect tuberculosis with sophisticated new technologies, as well as educating 700 health care workers on tuberculosis diagnostic guidelines, according to an article on their website. These figures represent improvement, but the fight will not end without help from allies abroad.

International Efforts Against Tuberculosis

Combatting tuberculosis in Timor-Leste requires support. By providing the resources necessary to make health care accessible, hundreds of lives can be saved every year. With this in mind, on June 11, 2026, Senators Jeanne Shaheen (New Hampshire) and Todd Young (Indiana) officially reintroduced the End Tuberculosis Now Act. The bipartisan bill would make tuberculosis elimination a U.S. foreign-assistance priority and strengthen coordination around research, diagnosis, treatment and prevention.

Senator Young stated: “Tuberculosis is preventable, treatable and curable, yet it continues to claim far too many lives around the world. The End Tuberculosis Now Act will strengthen efforts to expand access to diagnosis and treatment, support the development of new tools and vaccines and improve our ability to detect and respond to future infectious disease threats. By helping countries combat tuberculosis before it spreads further, we can save lives, strengthen global health security and better protect Americans from emerging infectious diseases.”

It remains to be seen whether Congress will pass the bill. The legislation is one example of international policy efforts aimed at reducing the global burden of tuberculosis.

– Madison Hoar

Madison is based in Birmingham, AL, USA and focuses on Global Health for The Borgen Project.

Photo: Flickr

October 3, 2026
https://borgenproject.org/wp-content/uploads/borgen-project-logo.svg 0 0 Lynsey Alexander https://borgenproject.org/wp-content/uploads/borgen-project-logo.svg Lynsey Alexander2026-10-03 07:30:422026-10-02 13:04:40The Fight Against Tuberculosis in Timor-Leste
Disease, Global Health, Global Poverty

Fish Could Help Reduce Schistosomiasis in Senegal

Schistosomiasis in SenegalIn a study with implications that could change the fight against poverty in rural Senegal, researchers working along the northern Senegal River basin found an unexpected solution to schistosomiasis in Senegal. The parasite, which disproportionately affects those facing extreme poverty, may be reduced through native fish.

Schistosomiasis, a snail-borne disease, spreads when parasite larvae released by freshwater snails penetrate the skin during contact with infested water. The resulting symptoms include abdominal pain, diarrhea, liver enlargement and kidney damage. In children, schistosomiasis can cause anemia and affect health and school attendance. An affordable solution to schistosomiasis in Senegal was found close to home, or more accurately, in rice fields. This shows researchers that when examining causes and effects of global poverty, they may not need to look far for a solution.

Neglected Tropical Disease in Senegal

Schistosomiasis is a type of neglected tropical disease, or NTD. More well-known NTDs include leprosy and rabies, but these diseases share one important fact: they disproportionately affect those in poverty. It is estimated that NTDs affect more than a billion people, with schistosomiasis prevalent in tropical and subtropical areas.

Those more likely to be infected include children who swim or play in infested water and farmers and fishers whose work brings them into regular contact with freshwater. Control of schistosomiasis relies on prevention and treatment, including preventive chemotherapy, access to safe water, improved sanitation, behavior change and snail control.

Solution of Native Fish

Researchers working along the northern Senegal River basin studied how releasing native freshwater fish in rice paddy fields could reduce the risk of schistosomiasis. The two fish, African bonytongue and Nile tilapia, thrived in the fields, even without researchers actively feeding them. Eating infected snails and competing with them for resources naturally decreased the snail population. After the release of native fish, researchers observed that paddy fields with fish carried fewer parasite-hosting snails. This could reduce the risk of infection for farmers and their families.

The effects of African bonytongue and Nile tilapia are threefold: reducing the risk of infection; improving soil nutrients and increasing rice yields by more than 25 percent; and providing farmers with an additional potential source of income through fishing.

Final Thoughts

The causes and effects of poverty are often cyclical. A health condition can create financial pressure that contributes to poverty, while poverty can increase vulnerability to health conditions. Addressing multiple elements of global poverty is necessary to find a solution. A cost-effective approach such as releasing native fish into rice paddy fields could have wide-reaching, multidimensional effects. While it does not replace serious funding, treatment and infrastructure changes, finding simple, affordable and effective solutions can make a difference.

Researchers are now exploring how rice-fish farming can be expanded across more farms in Senegal.

– Madalyn Youngbauer

Madalyn is based in Worcester, MA, USA and focuses on Good News and Global Health for The Borgen Project.

Photo: Wikimedia Commons

September 27, 2026
https://borgenproject.org/wp-content/uploads/borgen-project-logo.svg 0 0 Lynsey Alexander https://borgenproject.org/wp-content/uploads/borgen-project-logo.svg Lynsey Alexander2026-09-27 01:30:162026-09-26 22:40:53Fish Could Help Reduce Schistosomiasis in Senegal
Developing Countries, Disease, Global Poverty, Health

How Telemedicine Expands Healthcare in Rural Pakistan

Healthcare in Rural PakistanFor a patient living in a remote Pakistani community, seeing a doctor can require more than making an appointment. Long distances, transportation costs and limited access to specialists can make healthcare difficult to reach, especially for lower-income families. Telemedicine in Pakistan offers one solution by connecting patients with healthcare professionals through digital platforms and remote consultations.

Pakistan has begun moving telemedicine beyond individual online consultations and into local health facilities. Recent government initiatives show how digital health can connect rural communities with doctors while allowing nurses and other health workers to provide support on the ground. Here is more information about how telemedicine is expanding healthcare access in rural Pakistan.

Why Rural Communities Need Better Healthcare Access

Healthcare access in rural Pakistan is challenging due to significant barriers. The World Bank estimates that about 60.5% of Pakistan’s population lived in rural areas in 2025. Rural communities also experience higher poverty rates than urban communities, which makes the cost and accessibility of health services especially important.

For some rural patients, reaching a hospital or specialist requires a long journey. Transportation costs can add another burden for families with limited incomes. For people living in poverty, the cost of traveling to a distant hospital can also mean sacrificing money needed for food or other household necessities. Workers who depend on daily wages may also lose income when they have to spend a day traveling for medical care. These barriers can discourage people from seeking care or cause them to delay treatment.

Healthcare costs can create an additional burden for low-income families. According to the World Bank, poverty remains significantly higher in rural areas than in urban areas of Pakistan. Improving access to healthcare is therefore important not only for people’s health but also for protecting vulnerable families from additional financial pressure.

Telemedicine can address part of this problem. A 2024 study in “Frontiers in Public Health” found that telehealth can reduce travel-related costs and time while improving access to healthcare for people in rural and isolated areas.

How Telemedicine Brings Doctors Closer

Telemedicine allows patients to communicate with doctors without traveling to a distant hospital for every consultation. Depending on the service, patients can discuss symptoms, receive medical advice and access follow-up care through video calls or other digital platforms.

Sehat Kahani, a Pakistani digital health organization, uses a nurse-assisted e-clinic model to connect patients in underserved communities with doctors remotely. Nurses can assist patients at local clinics while doctors provide consultations through digital platforms.

The model also creates opportunities for doctors to serve patients from a distance. Sehat Kahani’s network includes thousands of doctors and its digital platform has delivered about 1 million consultations, according to 100X Impact Accelerator. The organization reports that women make up a majority of its trained doctors, including women who have returned to medical practice through flexible telehealth work.

This approach can address two problems at once: communities gain access to doctors while qualified medical professionals can provide care without working from a traditional hospital or clinic.

Pakistan Expands Digital Healthcare

Pakistan’s government has recently taken steps to integrate telemedicine into primary healthcare.

On Jan. 6, 2026, the Ministry of National Health Services, Regulations and Coordination worked with Sehat Kahani to launch a paperless, telemedicine-enabled Basic Health Unit in Gokina, Islamabad. The center uses secure video consultations, electronic medical records, digital prescriptions and pharmacy management systems. Nurses at the facility help patients through consultations and follow-up care.

The government expanded this effort on Jan. 14, 2026, when the Federal Health Minister inaugurated another digitalized telemedicine center at Bhambar Tarar near Islamabad. The Ministry of Health reported that the area had a Basic Health Unit but lacked a posted doctor. Residents previously needed more than an hour to reach major hospitals in Islamabad.

The new center allows residents to receive medical consultations locally. Health workers can also refer patients who need more advanced treatment to tertiary hospitals.

The government also announced an agreement with Sehat Kahani under which 5,000 online doctors will provide remote consultations. The government has described telemedicine as a permanent part of Pakistan’s national healthcare system and plans to establish 10 telemedicine centers.

A Solution With Room To Grow

Telemedicine cannot replace every form of medical care. Doctors still need to examine some patients in person and communities need reliable internet access, digital devices and trained health workers to use telemedicine effectively.

However, Pakistan’s recent initiatives show how the country can combine digital services with local health facilities. Instead of requiring every patient to travel to a major city, a local health center can connect patients with doctors elsewhere while nurses provide in-person support.

Telemedicine in Pakistan can also help reduce some of the financial burden associated with traveling long distances for healthcare. For low-income families, avoiding unnecessary transportation expenses and reducing time away from work can make medical consultations more accessible.

Sehat Kahani’s experience also shows that telemedicine can operate at scale. Its platform has already delivered about 1 million consultations while its network of doctors continues to connect patients with medical professionals across Pakistan.

Looking Ahead

As Pakistan expands its digital health infrastructure, telemedicine in Pakistan can help reduce some of the geographic and financial barriers that affect underserved communities. By bringing qualified doctors closer to patients through technology, Pakistan can move toward a healthcare system where access depends less on a person’s location or ability to travel and improve healthcare access in rural Pakistan.

– Afia Atif

Afia is based in Chenab Nagar, Pakistan and focuses on Technology and Global Health for The Borgen Project.

Photo: Wikimedia Commons

September 4, 2026
https://borgenproject.org/wp-content/uploads/borgen-project-logo.svg 0 0 Jennifer Philipp https://borgenproject.org/wp-content/uploads/borgen-project-logo.svg Jennifer Philipp2026-09-04 03:00:322026-09-04 02:18:14How Telemedicine Expands Healthcare in Rural Pakistan
Disease, Global Poverty, Health

Malaria Vaccination Program in Rwanda Helps Families in Poverty 

Malaria Vaccination Program in RwandaThe consequences of malaria have recently continued to affect the lives of families across Rwanda. According to the World Food Programme (WFP) poverty affects 27.4% of Rwanda’s population. Being sick with this life-threatening disease can result in lost income due to absence from work, which is detrimental, as Rwandan’s household savings are essential to spend on treatment from clinics. The lack of the benefit of earning a household income has led to financial strain on Rwandan families and pushed them into extreme poverty. Nevertheless, the new malaria vaccination program in Rwanda has helped families out of poverty. Organizations such as GAVI and UNICEF fund this free rollout, which can secure domestic incomes and give families an opportunity for financial security.

Malaria’s Impact on Household Incomes

 Malaria has imposed an economic burden on Rwanda. The Rwanda Biomedical Center (RBC) has reported an increase in malaria prevalence in Rwanda, with the disease affecting 76 people per 1,000 population—equivalent to 7.6%—in the 2024/2025 period, up from 4.5% recorded in 2023/2024. This has reduced the country’s economic growth, as families struggle with higher costs for essential goods and services and lack basic needs, which will inevitably push them into deeper poverty. As seen in high-deprivation regions, the price of food, transportation and school equipment amplifies the strain on low household incomes. This situation forces families to choose between medical care and necessities. This situation can decrease Rwanda’s economy and lead to a lack of internal wealth that affects trade, infrastructure and levels of employability.

Government-Led Immunization Strategy

 Nevertheless, Rwanda’s Ministry of Health began its malaria vaccine program in 2024. RBC figures show that in 2025/2026, malaria cases stood at 928,616, down from 1,131,314 in 2024/2025, indicating a recent decline after the previous surge. Thus, the Ministry of Health integrated the vaccine into childhood immunization to ensure households can access jabs at local Rwandan clinics without transportation costs.

 Experts say this will help reduce malaria cases in Rwanda, with improvements reported in mid-2026. In Rwanda, national childhood vaccination coverage is at 95%, yet gaps persist in reaching last-mile and hard-to-reach populations. Community Health Workers (CHWs) play a critical role in promoting and delivering vaccination services at the community level. This majority of vaccinated children reduces emergency appointments at clinics and financial strain on households.

GAVI and UNICEF’S Role

Since 2024, Gavi has played a significant role in the new malaria vaccination program in Rwanda. Gavi introduced the malaria vaccines RTS,S and R21/Matrix-M through procurement deals that enabled Rwanda to access affordable malaria vaccines while reducing hospitalizations. Gavi’s website stated that “[a]ccording to WHO estimates, the vaccine saves 1 life for every 200 children vaccinated.” Here, Gavi partnered with UNICEF to subsidize the entire cost, making the malaria vaccine free to every Rwandan child. Gavi financing the vaccine and UNICEF procuring it, with the Rwandan Ministry of Health delivering it through immunization, benefits every Rwandan citizen by protecting them from financial strain.

Vaccination Produces Widespread Economic Benefits

Recent results from the new malaria vaccination program in Rwanda show that it has directly reduced poverty across the country. The Rwandan government’s relationship with the organization Gavi has helped communities access life-changing protection that keeps children and adults safe while preventing families from extreme medical costs. This organization shows how international interventions can lift deprived countries out of poverty while strengthening national economic development.

– Alexandra Eaton

Alexandra is based in Birmingham, UK and focuses on Global Health for The Borgen Project.

Photo: Unsplash

September 2, 2026
https://borgenproject.org/wp-content/uploads/borgen-project-logo.svg 0 0 Jennifer Philipp https://borgenproject.org/wp-content/uploads/borgen-project-logo.svg Jennifer Philipp2026-09-02 03:00:292026-09-02 04:00:32Malaria Vaccination Program in Rwanda Helps Families in Poverty 
Disease, Global Poverty

From Polio to Lassa Fever in Nigeria

Lassa Fever in NigeriaIn August 2021, the World Health Organization (WHO) declared Nigeria free of wild polio. The virus was responsible for hundreds of deaths each year. Nigeria eradicated the disease through the implementation of public health systems and educational programs. Health experts tracked the disease by developing organized health systems and data trackers, and by testing wastewater for contaminants to catch outbreaks early. Mobile vaccine clinics also helped mobilize thousands of young children, and educational programs taught communities how to avoid the virus through sanitization. The fight against polio expanded the capacity of Nigeria’s healthcare systems and taught health experts essential methods for fighting disease. Not only was polio eradicated, but Nigeria gained a skill set to protect its population from future diseases.

Lassa Fever in Nigeria

Lassa fever was first recognized in 1969 in Lassa, Nigeria. In 15% of extreme cases, victims develop severe symptoms such as bleeding from mucus membranes and accumulation of fluid in the lungs. This leads to a 15-25% mortality rate. The multimammate rat, one of the most common rodents in the region, carries the disease and contaminates all who come into close contact with it or its secretions. Contaminated individuals can then transmit Lassa fever through feces, urine, blood and saliva. This makes the disease highly contagious, particularly in rodent reservoirs or communities with large rodent populations.

The Deadly Consequences of Poverty

Most causes of Lassa fever can be traced to poor sanitation practices and poor infrastructure that allow for close habitation with rodent populations. This means that Lassa fever primarily affects Nigerians in poverty. In Nigeria, 122 million people live in poverty. Further, 57 million people lack access to safe water, and 130 million lack adequate sanitation. Despite these high numbers, only 3.5% of the national budget goes toward public health. This allows diseases like Lassa fever to predominantly affect the most vulnerable or those in poverty. Impoverished communities are far more susceptible to the spread of the disease, and educational and resource barriers make the consequences of contamination catastrophic.

Lassa Fever Today

Nigeria’s Centre for Disease Control and Prevention (CDC) reported 1,000 confirmed Lassa fever cases and 237 deaths as of late July 2026. That marks a case fatality rate of 23.7%, well above the 18.8% recorded during the same period in 2025. The outbreak has spread across 23 states, though roughly 86% of confirmed cases remain concentrated in five states: Ondo, Bauchi, Taraba, Edo and Benue. The situation continues to evolve week by week.

Despite the gravity of the outbreak, Nigeria is better prepared thanks to lessons learned in combating wild polio. Humanitarian funding sponsored health care systems support and vaccination efforts during the polio fight, and a similar pattern is now emerging in the response to Lassa fever.

The Global Polio Eradication Initiative

The Global Polio Eradication Initiative (GPEI), a partnership between aid groups such as WHO, United Nations Children’s Fund (UNICEF) and the CDC, has transitioned its services toward helping with Lassa fever outbreaks in Nigeria. The initiative developed surveillance systems to track polio, vaccine distribution methods to help eradicate the disease, and integration systems to inform communities about the importance and safety of vaccinations. GPEI now uses these same methods and systems to efficiently fight Lassa fever. Knowledge gained from the polio fight has helped organizations like GPEI and the Nigerian government track the disease’s progress through data systems and wastewater testing, identify at-risk communities, and educate people on health care and sanitization. These methods cannot ensure the immediate eradication of Lassa fever, but Nigeria’s experience fighting disease allows for more efficient solutions than those used during prior epidemics.

Other Humanitarian Aid Groups

The Sanitas Health and Development Foundation has committed more than $860,000 to provide structural support to health care organizations, help strategically plan the public health sector, and organize technological health systems to improve outcomes. These donations will enable better systems to track and defeat Lassa fever. The Hope Compassion and Mercy Foundation has separately committed $280,000 toward the cause. Its funding will go toward training health care workers, funding mobile clinics and rehabilitating or constructing permanent health care clinics for lasting impact.

Aid’s Impact

The fight against deadly viruses in Nigeria is becoming more manageable as vaccinations become more universal and experience in fighting diseases grows. More Nigerians trust routine medical work, and more vaccine clinics have emerged in remote regions. These clinics offer wider access to treatments for ailments such as pneumonia, diarrhea, malaria and Human Immunodeficiency Virus (HIV), in addition to vaccinations against diseases such as polio, measles, Ebola and Lassa fever.

Nigeria has faced a long history of deadly diseases, with those in poverty the most vulnerable. That history is tragic, but it also offers hope for a future where deadly viruses can be defeated. Lessons from the fight against polio have made the response to Lassa fever more efficient and effective, and the international humanitarian community continues to show dedicated efforts to aid the response.

– Aubrey Wallen

Aubrey is based in Alexandria, VA, USA and focuses on Global Health for The Borgen Project.

Photo: Flickr

August 22, 2026
https://borgenproject.org/wp-content/uploads/borgen-project-logo.svg 0 0 Lynsey Alexander https://borgenproject.org/wp-content/uploads/borgen-project-logo.svg Lynsey Alexander2026-08-22 01:30:302026-08-20 11:59:28From Polio to Lassa Fever in Nigeria
Disease, Global Poverty, Health

Diseases Impacting Venezuela

Diseases Impacting VenezuelaOutbreaks of infectious diseases are the primary health challenges impacting the population and shelter infrastructure in Venezuela. A June 24, 2026, 7.2 magnitude earthquake along Venezuela’s northern coast affected people significantly, along with a subsequent 7.5 magnitude earthquake that killed 32 people, injured 700 people and devastated areas as distant as La Guaira state 160 km east. The earthquakes impacted 1.7 million buildings resulting in widespread power outages across several states.

Of Venezuela’s 31.7 million population, 20 million (63.1%) already lived in poverty, population susceptibility to contracting infectious diseases was high due to no government epidemiological bulletin publications since 2016 and early economic loss predictions outlines costs of 7% of Venezuela’s $111 billion GDP. Structural losses immediately exacerbated the issue of infectious diseases impacting Venezuelan earthquake victims through eliminating their access to water, sanitation and hygiene (WASH) facilities, healthcare workers, hospitals, adequate medical care and nutritious food. Increasing earthquake victims’ susceptibility to infectious diseases such as measles, dengue and yellow fever, malaria, diarrhea and skin infections.

Concerns

  • Infectious Disease Treatment Challenges: Medical care services have been sparse due to the impact of the earthquakes on regional healthcare facilities and the fact that they were already 37% short of essential medicines following years of poor economic investment. A Pan-American Healthcare Association (PAHO) analysis showed that more than 50 hospitals in seven states are still functioning but that many facilities experienced critical structural damage. Additionally, the earthquakes resulted in the evacuation of three hospitals, the damaging of 20 primary care units and overcrowding in healthcare facilities. Corpse remains have also led to disease outbreaks and contamination risks.
  • Rising Fatality and Victim Rates: The Los Angeles (LA) Times reported that Venezuela’s health system, which was already weakened by an eight-year economic depression leading to the departure of more than half of the nation’s doctors and other skilled health professionals, had, by July 11, 2026, helped elevate the earthquake’s death toll to 3,800, with 16,700 people injured.
  • Infrastructure Damage: The earthquake destruction zone now presents economic challenges at an estimated $37 billion in losses, including $24 billion in housing and healthcare damage, $13 billion worth of mostly road and energy generation infrastructure damage, meaning 650,000 people will need humanitarian assistance with approximately 17,000 left homeless. Economic disruption means costs will rise further and shelter and healthcare reconstruction efforts become heavily constrained by a pre-existing weak economy.

Solutions

  • Imminent Infectious Disease Treatment: UN subsidiaries have sent 68 tonnes of medical, WASH and household supplies, alongside contributing primary healthcare services through distributing hygiene kits and further sanitation infrastructure fueled by $306 million worth of funding from The Humanitarian Response Plan for Venezuela and private-sector donations.
  • Managing Fatality and Victim Rates: PAHO has presently recovered 6,400 people by concentrating on early recovery, mobilizing emergency specialist expertise, providing health services such as sanitary post-mortem care, diagnostic imaging and immunizations, alongside pleas for a $24 million emergency fund to enable epidemiological surveillance in the earthquake destruction zone.
  • Remedying Regional Infrastructure Damage: La Guaira state sport complexes are providing their facilities as temporary logistics hubs for the storing of health, water and food aid. Their athletic facilities also offer shelter for thousands of displaced people. The United Nations High Commissioner for Refugees (UNHCR) is trying to sustain infrastructure advancements, “seeking $14.85 million to support up to 30, 000 people with shelter and essential aid over the next six months.”

Looking Ahead

June 2026 publications painted a grave picture of what presently, and in the future lay ahead for Venezuela, its pre-earthquake impoverished population of 20 million and its healthcare services. Earthquake destruction zone infectious disease challenges clearly reside, yet by both national and international aid recognizing this issue, prompt economic, shelter and medical relief has advanced future stability against the multitude of current factors that encourage the problem of infectious diseases impacting Venezuela. 

– Oliver Jones

Oliver is based in Cheshire, UK and focuses on Business and Global Health for The Borgen Project.

Photo: Flickr

August 2, 2026
https://borgenproject.org/wp-content/uploads/borgen-project-logo.svg 0 0 Jennifer Philipp https://borgenproject.org/wp-content/uploads/borgen-project-logo.svg Jennifer Philipp2026-08-02 07:30:322026-07-31 23:49:53Diseases Impacting Venezuela
Disease, Global Poverty, Health

3 Organizations Fighting Heart Disease in the Philippines

Heart Disease in the PhilippinesOne of the Philippines’ most common crises includes heart diseases like heart failure, hypertensive heart disease and ischemic heart disease. Cardiovascular disease causes one-third of deaths in the Philippines. An example of its impact is during a 6-month period from January to July in 2023, where doctors recorded more than 65,000 ischemic heart disease cases, accounting for 19% of all deaths. This has weakened many Filipinos’ immune systems, making them highly vulnerable. While this remains a severe challenge in the Philippines, three organizations have stepped up to the cause and started fighting heart disease in the country.

The Connection Between Poverty and Heart Disease

The link between poverty and heart disease is striking. As of 2023, 15.5% of the Filipino population lives below the national poverty line. The causes of cardiovascular disease include the inability to afford proper living conditions, limited access to food and dirty water — all challenges that low-income Filipinos face daily. They also confront another difficult sacrifice: a normal heart failure hospitalization in a private hospital costs about ₱42,000, which exceeds 10% of the average Filipino’s annual salary. The nation covers only some of this cost, forcing Filipinos to choose between survival and a long treatment. Research from the University of the Philippines highlights a shortage of doctors relative to the population, and too many cardiovascular disease patients receive diagnoses far too late for quality treatment. Here is information about three organizations fighting heart disease in the Philippines.

1. Children’s Heart Foundation

The Children’s Heart Foundation stands among several organizations working to change the lives of people with heart disease. It works to address heart problems so that future generations experience fewer cardiovascular diseases, improving global health. Volunteers founded it in 2000 and launched it with a fundraiser for a single cardiovascular patient. Since then, it has evolved into a nonprofit organization that serves low-income Filipinos tirelessly. It provides quality medical care for free, stopping many heart diseases before they turn fatal. Partnering with the Philippines Heart Center, the foundation delivers financial aid to those who need it most. It also builds a network connecting young and old patients, creating valuable social opportunities.

2. Gift of Life International

Gift of Life International provides care to children suffering from heart disease in the Philippines. This international organization receives requests to aid certain countries, with the greatest need coming from Manila. It has built strong partnerships with local groups and have saved more than 7,000 Filipino children. Gift of Life International pursues four main goals: securing donations, helping people with cardiovascular disease across multiple nations, handling incoming requests and managing volunteer involvement in ongoing efforts. This organization sets a strong example for others on how to improve healthcare access in the Philippines.

3. The Philips Foundation

The Philips Foundation also tackles the challenge of diagnosing cardiovascular heart disease early so that patients avoid fatal consequences. It raises awareness about global health across communities in the Philippines. Its plan involves training 200 teachers to identify students with cardiovascular diseases, a strategy that could save many lives by allowing teachers to spot warning signs early and enable sooner treatment. Using techniques like handheld ultrasound screeners, the program reaches areas where no nearby medical facilities exist. In the future, this project could expand across the entire Philippines, inspiring further change in the fight against heart disease.

Looking Ahead

Certain organizations are driving real progress against heart disease in the Philippines. Through financial assistance, lifesaving surgery and innovative early detection tools, organizations like the Children’s Heart Foundation, Gift of Life International and the Philips Foundation are changing the numbers for heart disease patients in the Philippines. These efforts create safer and more equitable conditions for Filipinos and their future generations, proving that the fight against heart disease in the Philippines moves in the right direction.

– Brijesh Mohan

Brijesh is based in Kendall Park, NJ, USA and focuses on Global Health and Celebs for The Borgen Project.

Photo: Flickr

July 16, 2026
https://borgenproject.org/wp-content/uploads/borgen-project-logo.svg 0 0 Jennifer Philipp https://borgenproject.org/wp-content/uploads/borgen-project-logo.svg Jennifer Philipp2026-07-16 03:00:502026-07-15 12:51:333 Organizations Fighting Heart Disease in the Philippines
Page 1 of 76123›»

Get Smarter

  • Global Poverty 101
  • Global Poverty… The Good News
  • Global Poverty & U.S. Jobs
  • Global Poverty and National Security
  • Innovative Solutions to Poverty
  • Global Poverty & Aid FAQ’s
Search Search

Take Action

  • Contact Your Leader
  • Donate
  • 30 Ways to Help
  • Volunteer Ops
  • Internships
  • Courses & Certificates
  • The Podcast
Borgen Project

“The Borgen Project is an incredible nonprofit organization that is addressing poverty and hunger and working towards ending them.”

-The Huffington Post

Inside The Borgen Project

  • Contact
  • About
  • Financials
  • President
  • Board of Directors
  • Board of Advisors

Get Smarter

  • Global Poverty 101
  • Global Poverty… The Good News
  • Global Poverty & U.S. Jobs
  • Global Poverty and National Security
  • Innovative Solutions to Poverty
  • Global Poverty & Aid FAQ’s

Ways to Help

  • Contact Your Leader
  • Donate
  • 30 Ways to Help
  • Volunteer Ops
  • Internships
  • Courses & Certificates
  • The Podcast
Scroll to top Scroll to top Scroll to top



